top of page
Subscribe to EchoBridgeMD Pearls
Yes, sign me up to receive EchoBridge Pearls directly to my email inbox.
Expert Cardiac POCUS Pearls

by Stephen Alerhand MD
Our EchoBridgeMD Pearls provide concise, high-impact learning points for mastering advanced echocardiography and cardiac POCUS for the very next shift, rotation, or clinical practice day.
Educational pearls and media are intended for teaching purposes only and should not be interpreted as definitive diagnostic or management recommendations for individual patients.
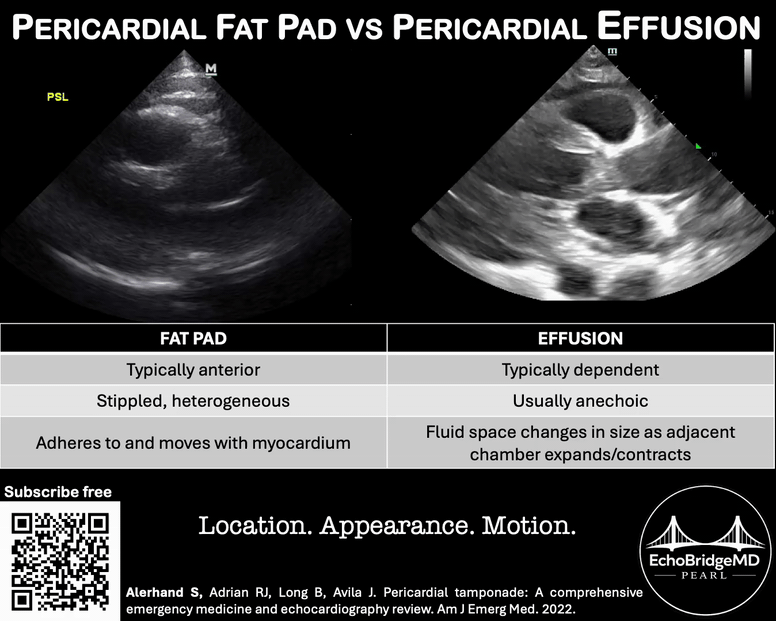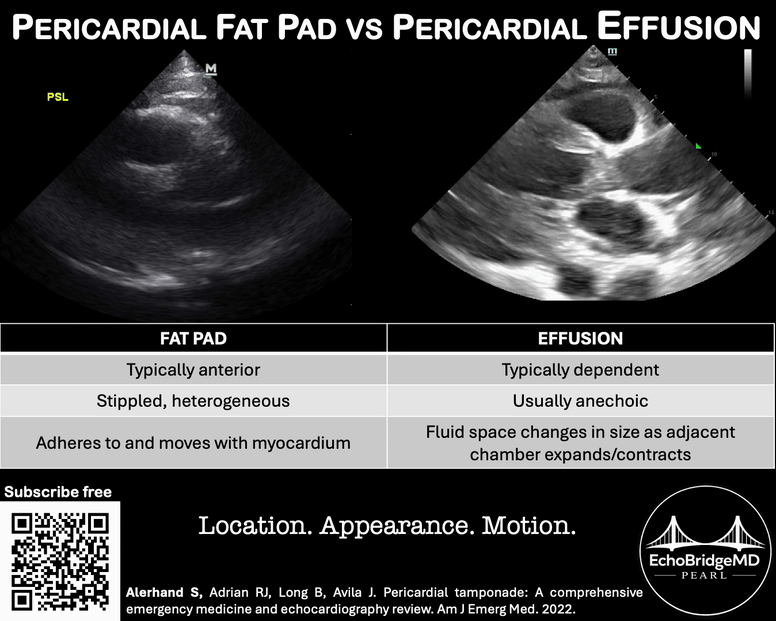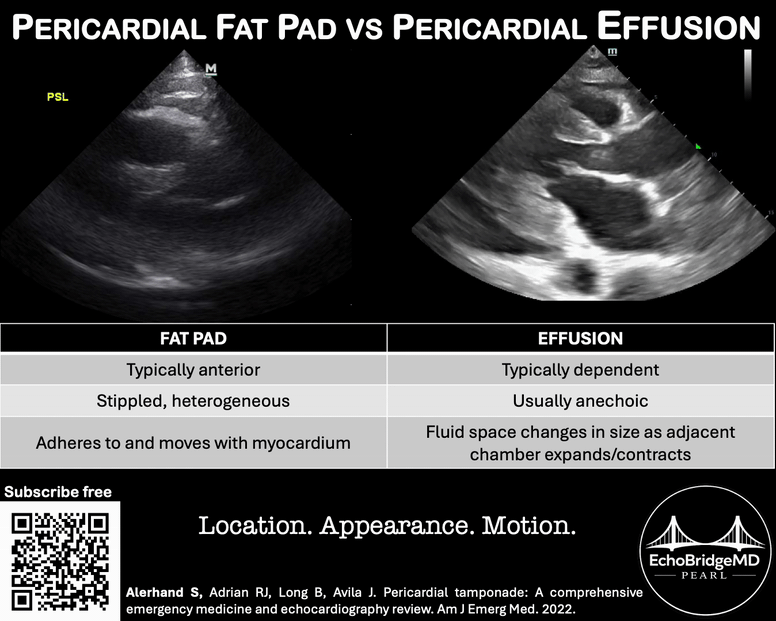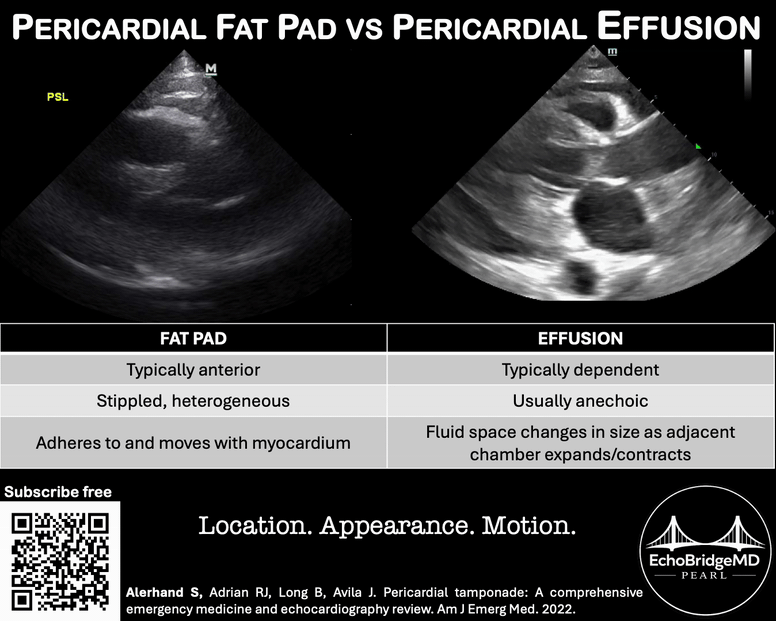
EchoBridgeMD Pearl #32: Pericardial Fat Pad vs Pericardial Effusion
A pericardial fat pad can mimic a pericardial effusion on echocardiography, but several features can help distinguish them. Pericardial fat typically has a stippled or heterogeneous appearance, is commonly located anteriorly in the atrioventricular groove, and adheres to the myocardium. As a result, it moves in synchrony with the heart throughout the cardiac cycle. In contrast, a pericardial effusion is usually anechoic and tends to collect in dependent portions of the perica

Stephen Alerhand
3 days ago1 min read


EchoBridge Pearl #24: Assessing Pericardial Effusions from Multiple Views
An effusion may be visible in one view but absent in another, and its apparent size can vary substantially depending on the imaging plane. Before determining the presence, size, or distribution of a pericardial effusion, systematically examine all standard cardiac windows to avoid underestimating or overestimating the effusion. In these clips, note how the pericardial effusion appears most prominent in the subxiphoid long-axis view. References: 📖 Alerhand S, Adrian RJ, Long
Stephen Alerhand
Sep 101 min read


EchoBridge Pearl #21: Tamponade Physiology in Cardiac Arrest
In patients with spontaneous circulation, systolic right atrial and diastolic right ventricular collapse are important echocardiographic signs of cardiac tamponade. During cardiac arrest, however, the absence of normal forward flow and intracardiac pressures makes these findings much less reliable. As a result, the presence or absence of right-sided chamber collapse should not be used in isolation to determine whether a pericardial effusion is responsible for the patient's ca
Stephen Alerhand
Aug 311 min read


EchoBridgeMD Pearl #15: POCUS Shortens Time to Pericardiocentesis
In patients with cardiac tamponade, earlier point-of-care ultrasound (POCUS) in the emergency department is associated with a shorter time to pericardiocentesis. Prompt bedside diagnosis can expedite definitive treatment in this life-threatening condition. References: 📖 Eke OF, et al. Timing of pericardiocentesis and clinical outcomes: Is earlier pericardiocentesis better? Am J Emerg Med. 2022. 📖 Alerhand S, Adrian RJ, Long B, Avila J. Pericardial tamponade: A comprehensive
Stephen Alerhand
Aug 101 min read


EchoBridgeMD Pearl #13: Pericardiocentesis for Cardiac Tamponade in Cardiac Arrest
Cardiac tamponade is one of the few potentially reversible causes of cardiac arrest. When a pericardial effusion is identified during cardiac arrest and the clinical presentation raises suspicion for tamponade physiology, emergent pericardial drainage should be performed. In one study, patients undergoing pericardiocentesis for suspected tamponade during cardiac arrest had a substantially higher survival to hospital discharge than all other patients (15% vs. 1%), highlighting
Stephen Alerhand
Aug 31 min read


EchoBridgeMD Pearl 12: Pathophysiology of Cardiac Tamponade
The development of cardiac tamponade depends more on the rate of pericardial fluid accumulation and pericardial compliance than on the absolute size of the effusion. With an acute pericardial effusion, the pericardium has not had time to stretch, so even 50 mL of rapidly accumulating fluid may produce tamponade physiology. In contrast, a chronic pericardial effusion allows the pericardium to gradually increase its compliance, permitting up to 2 liters of fluid to accumulate b
Stephen Alerhand
Jul 301 min read
bottom of page