top of page
Subscribe to EchoBridgeMD Pearls
Yes, sign me up to receive EchoBridge Pearls directly to my email inbox.
Expert Cardiac POCUS Pearls

by Stephen Alerhand MD
Our EchoBridgeMD Pearls provide concise, high-impact learning points for mastering advanced echocardiography and cardiac POCUS for the very next shift, rotation, or clinical practice day.
Educational pearls and media are intended for teaching purposes only and should not be interpreted as definitive diagnostic or management recommendations for individual patients.
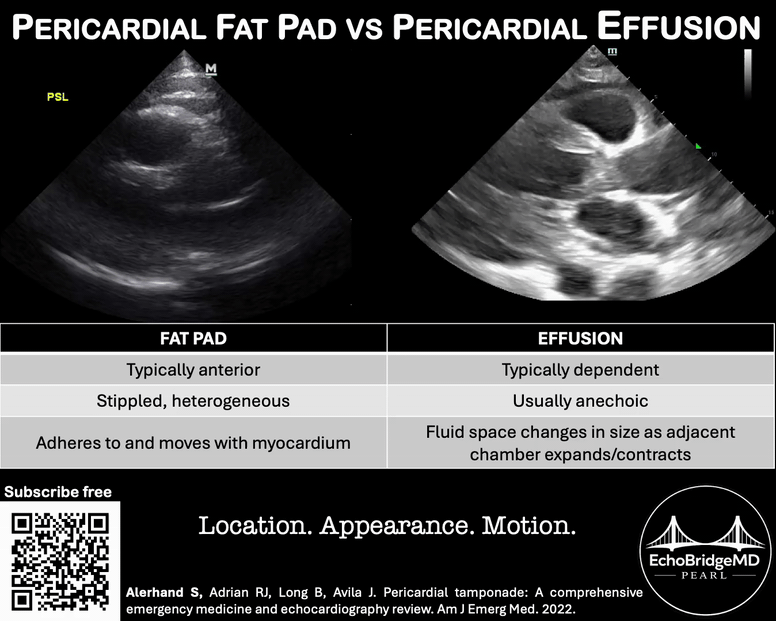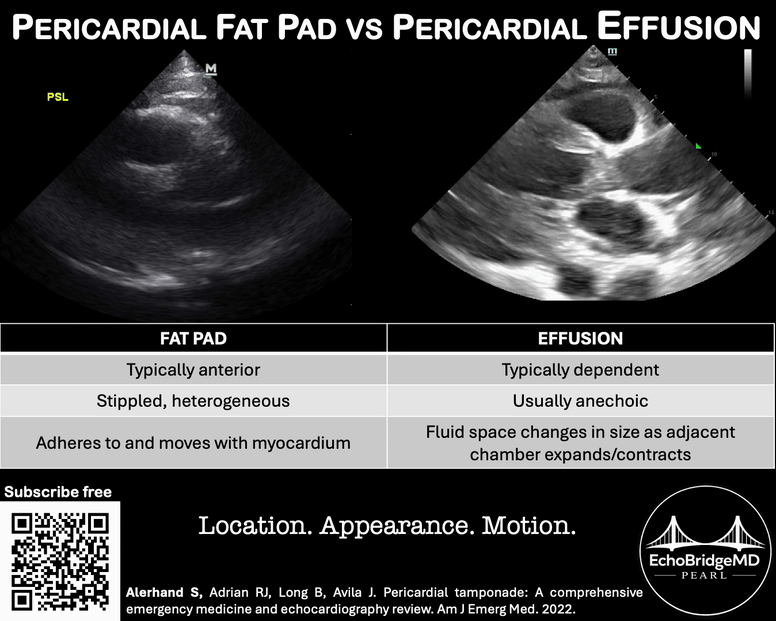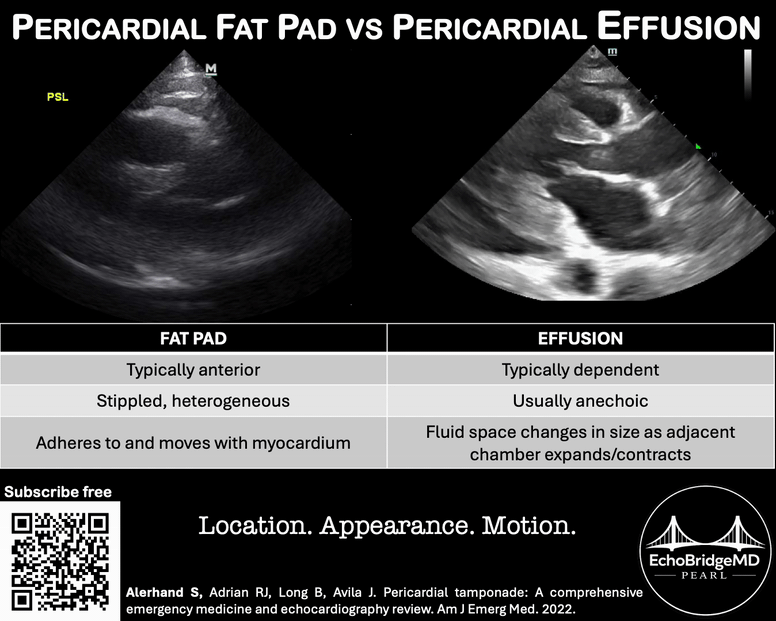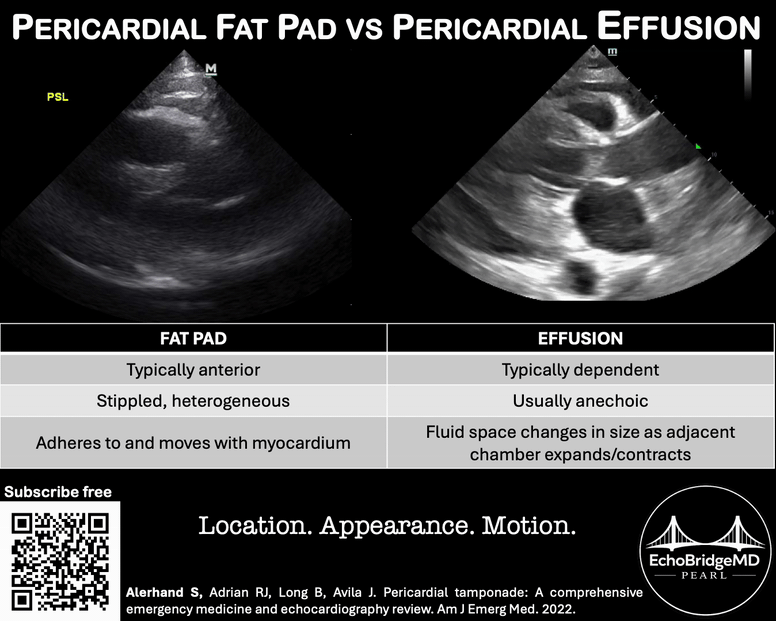
EchoBridgeMD Pearl #32: Pericardial Fat Pad vs Pericardial Effusion
A pericardial fat pad can mimic a pericardial effusion on echocardiography, but several features can help distinguish them. Pericardial fat typically has a stippled or heterogeneous appearance, is commonly located anteriorly in the atrioventricular groove, and adheres to the myocardium. As a result, it moves in synchrony with the heart throughout the cardiac cycle. In contrast, a pericardial effusion is usually anechoic and tends to collect in dependent portions of the perica

Stephen Alerhand
3 days ago1 min read


EchoBridgeMD Pearl #31: How to Measure RV Free Wall Thickness
Accurate measurement of right ventricular free wall thickness (RVFWT) requires careful image optimization. Decrease the imaging depth and position the RV free wall near the center of the screen, with the focal zone at the level of the wall. Because ultrasound provides superior spatial resolution in the axial plane, orient the free wall horizontally so that the calipers measure perpendicular to the wall. Measure RVFWT at end-diastole, when the RV is largest and the relaxed fre
Stephen Alerhand
6 days ago1 min read
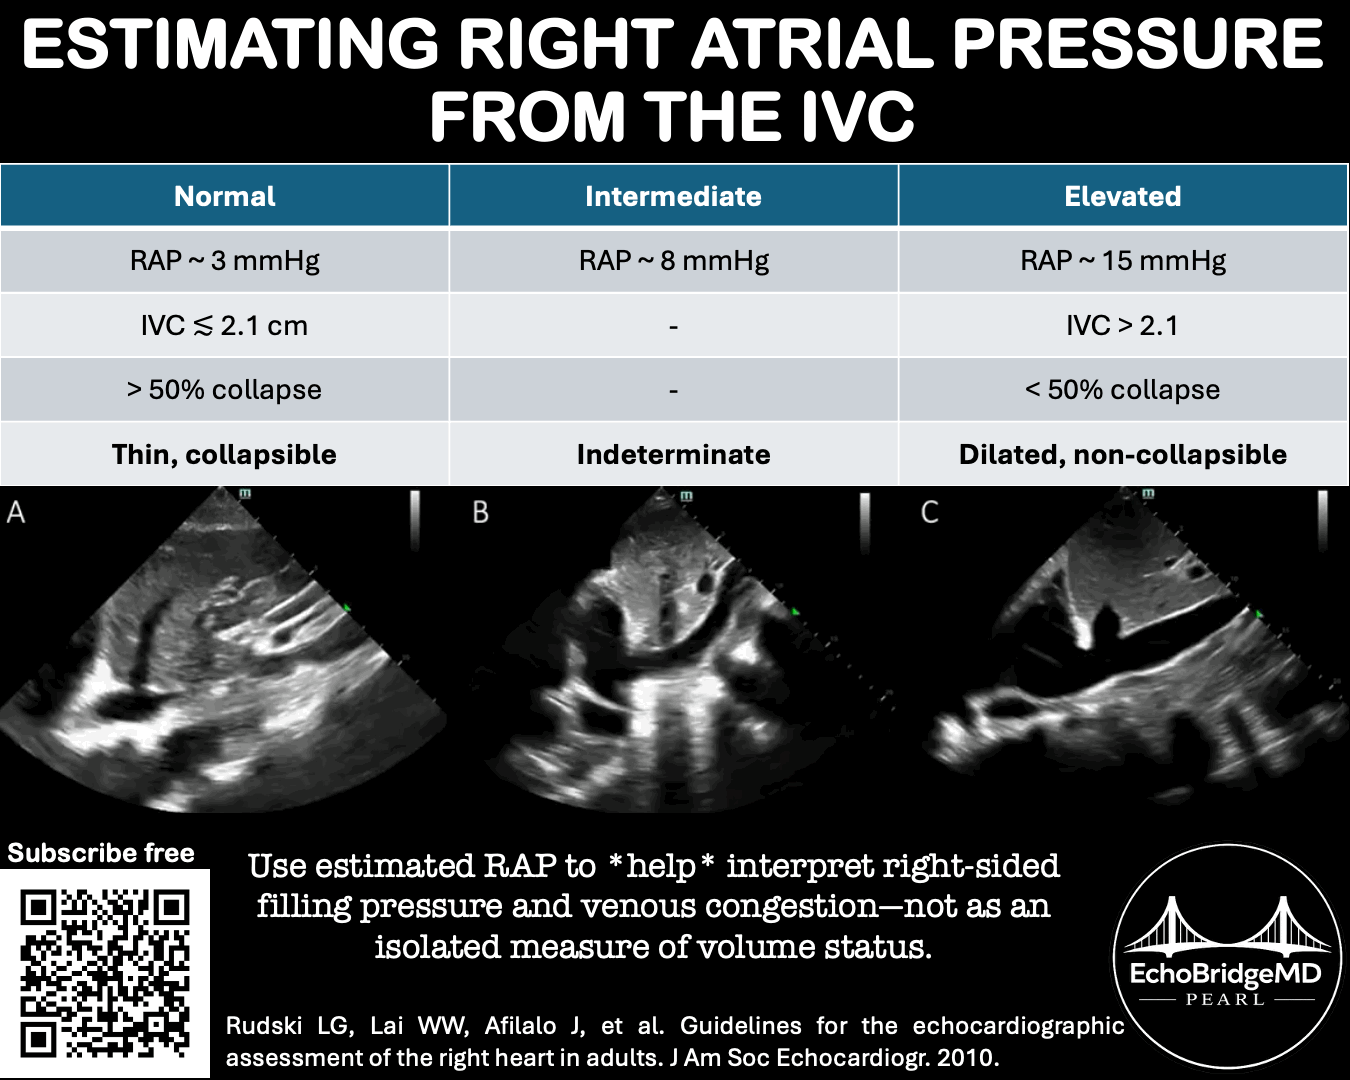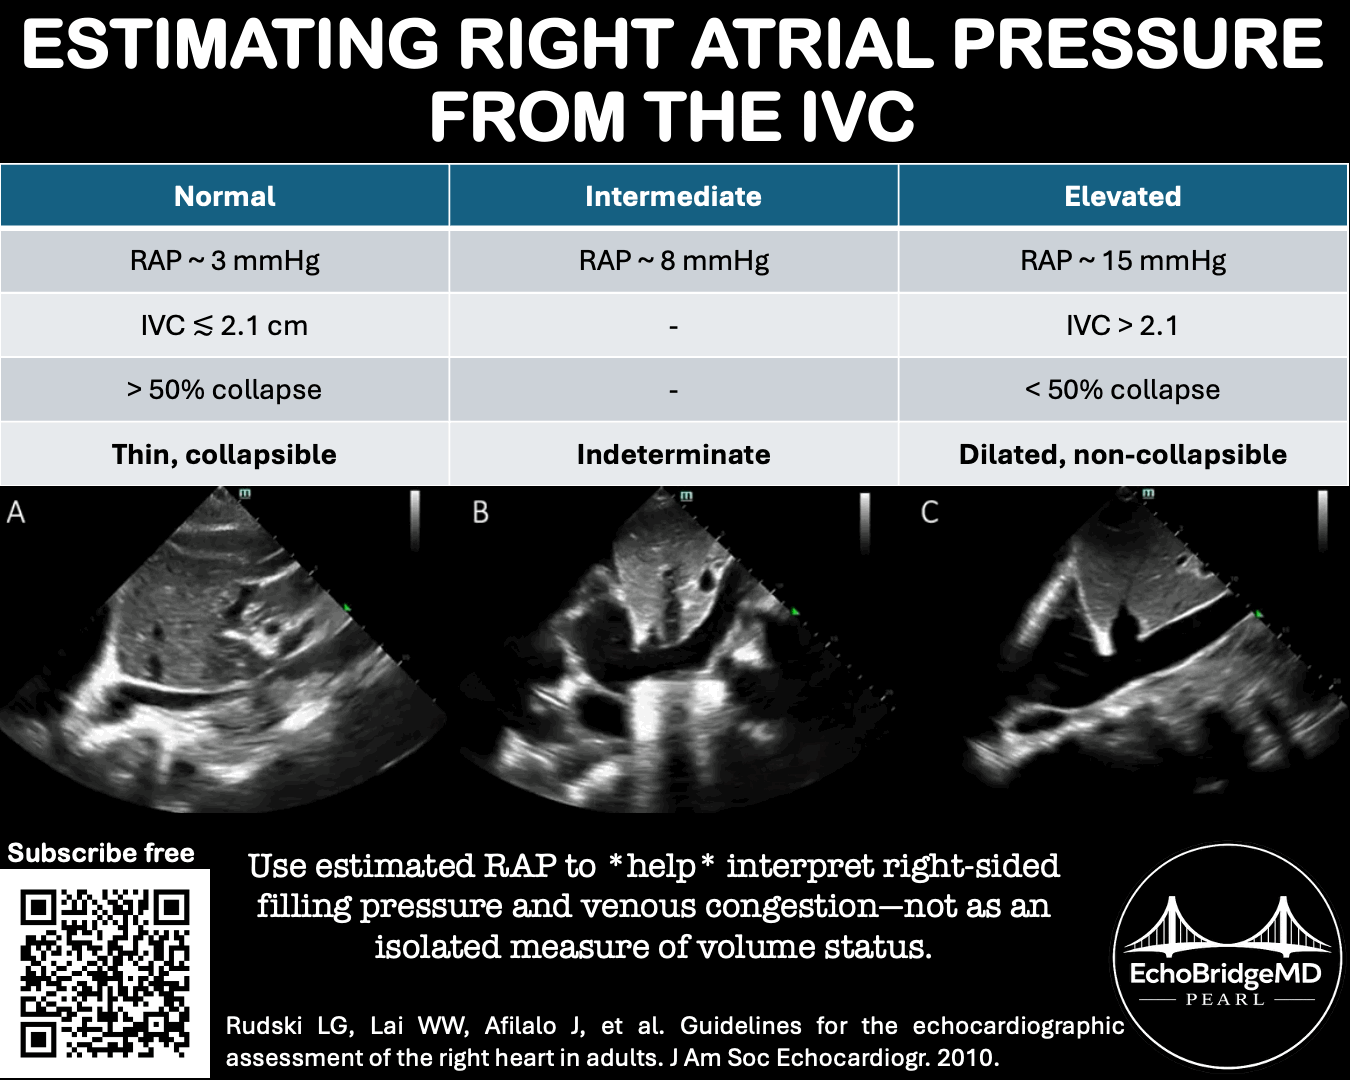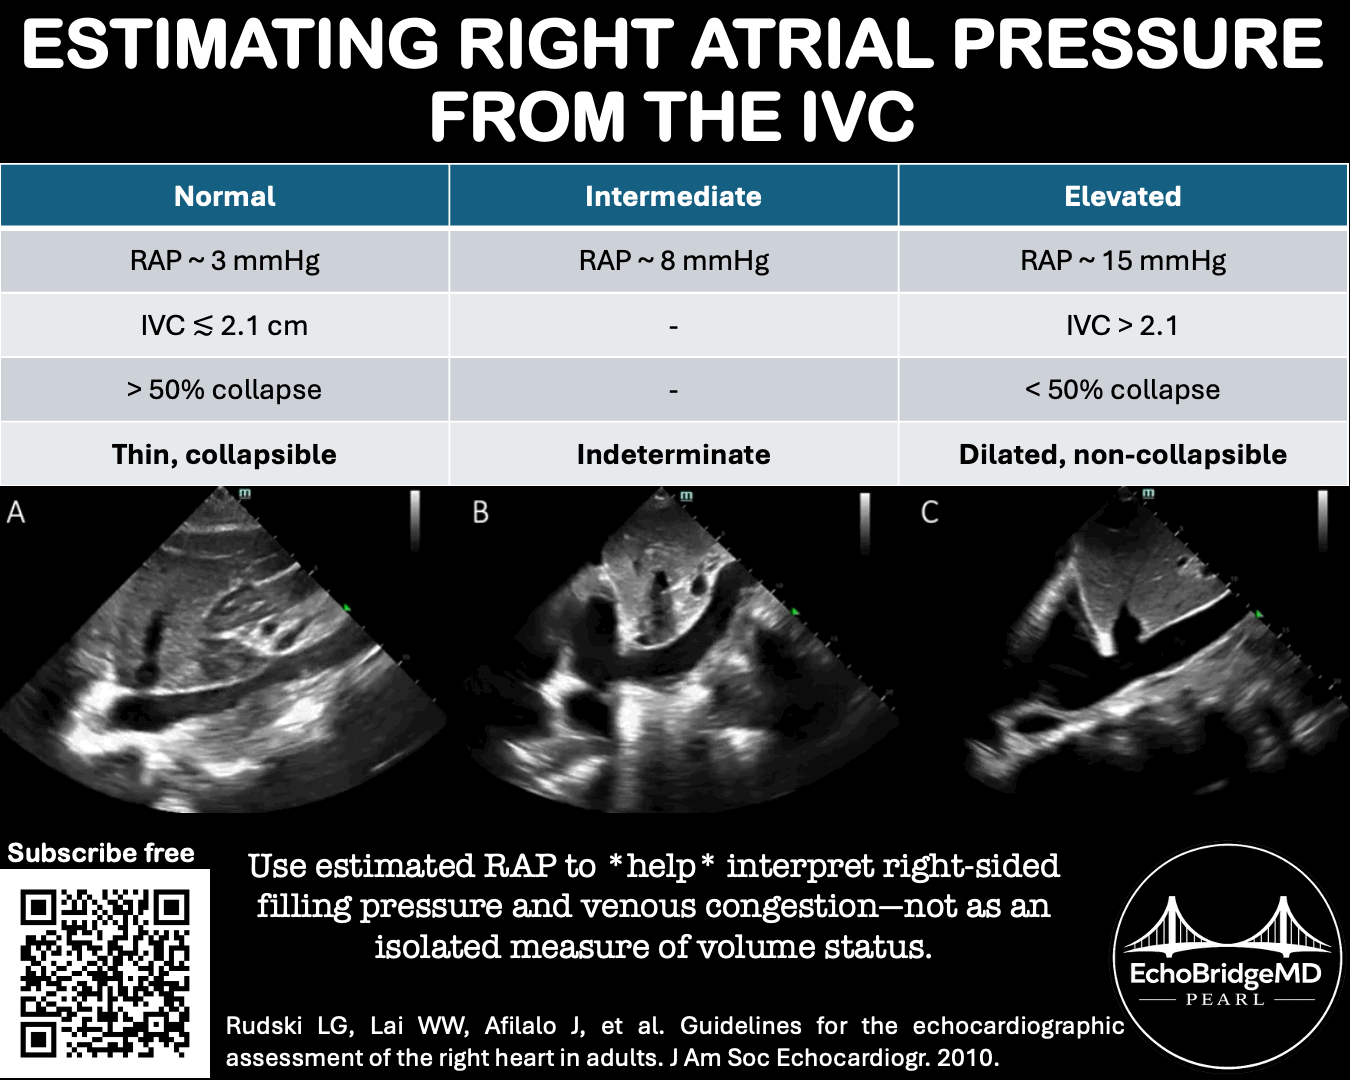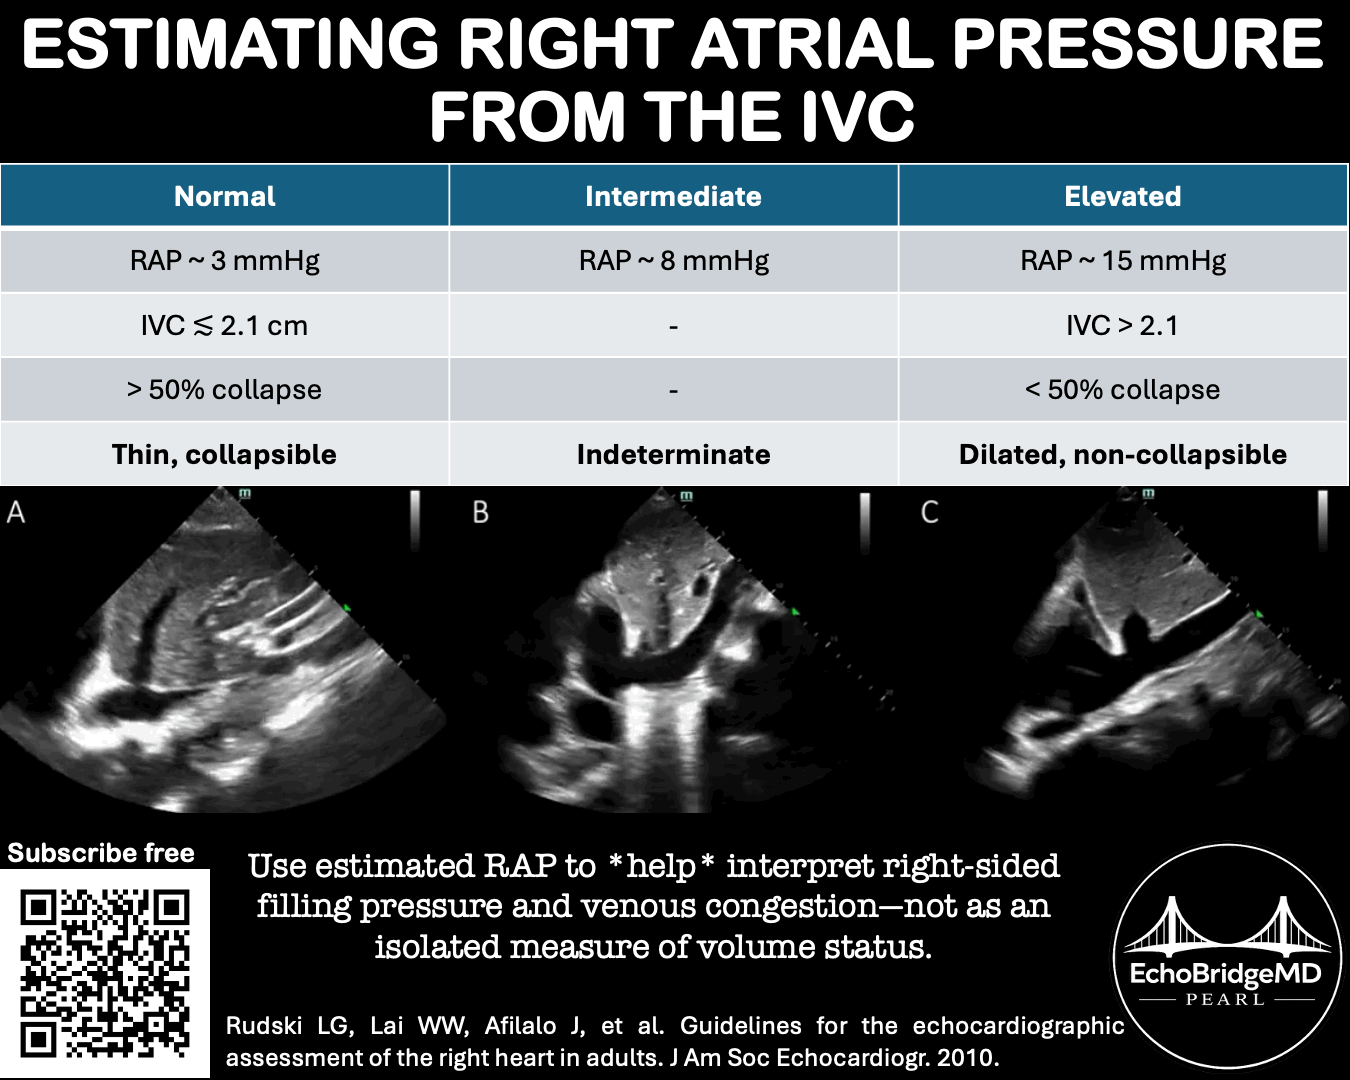
EchoBridgeMD Pearl #30: Estimating Right Atrial Pressure from the IVC
The American Society of Echocardiography recommends integrating inferior vena cava (IVC) diameter and inspiratory collapse to estimate right atrial pressure (RAP): • Normal RAP ≈ 3 mmHg (range 0–5): IVC ≤2.1 cm with >50% collapse during a sniff. • Intermediate RAP ≈ 8 mmHg (range 5–10): IVC diameter and inspiratory collapse do not fit either the normal or elevated RAP pattern. • Elevated RAP ≈ 15 mmHg (range 10–20): IVC >2.1 cm with <50% collapse during a sniff. At the bedsid
Stephen Alerhand
Oct 11 min read

EchoBridgeMD Pearl #29: Intracardiac Thrombus Can Form During Cardiac Arrest
Intracardiac thrombus can develop rapidly during cardiac arrest as a consequence of the low-flow state. In one study, new thrombus formation was observed approximately 6 minutes after the onset of cardiac arrest. Therefore, identifying a right-sided thrombus during resuscitation does not always mean that pulmonary embolism (PE) caused the arrest—particularly when the finding appears later in the resuscitation or after prolonged downtime. Nevertheless, a clot-in-transit with a
Stephen Alerhand
Sep 281 min read
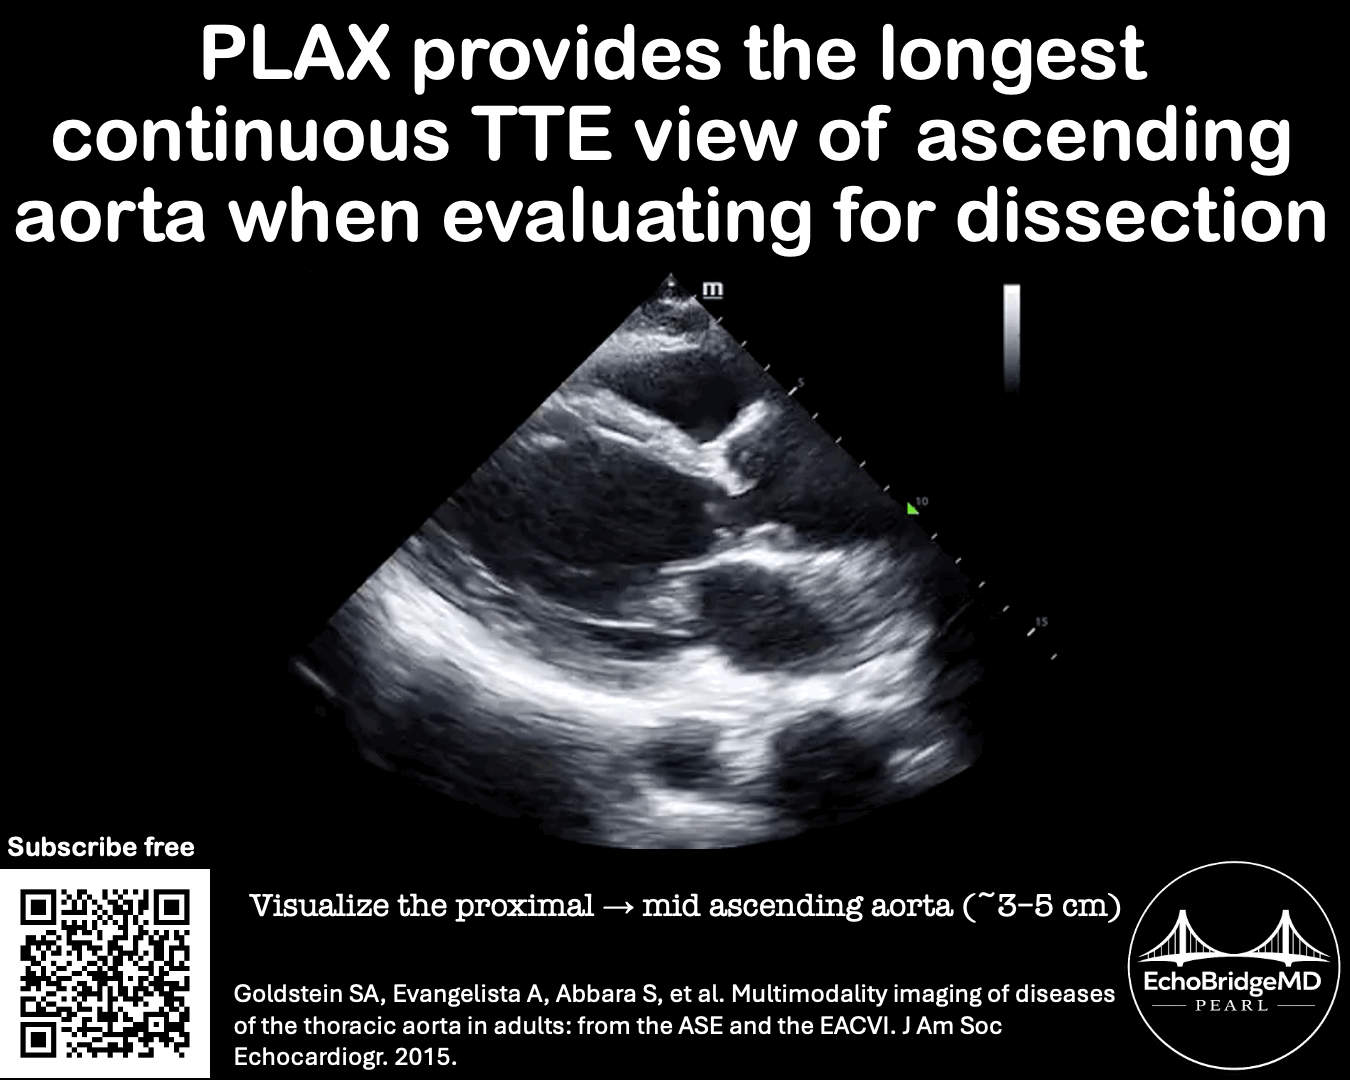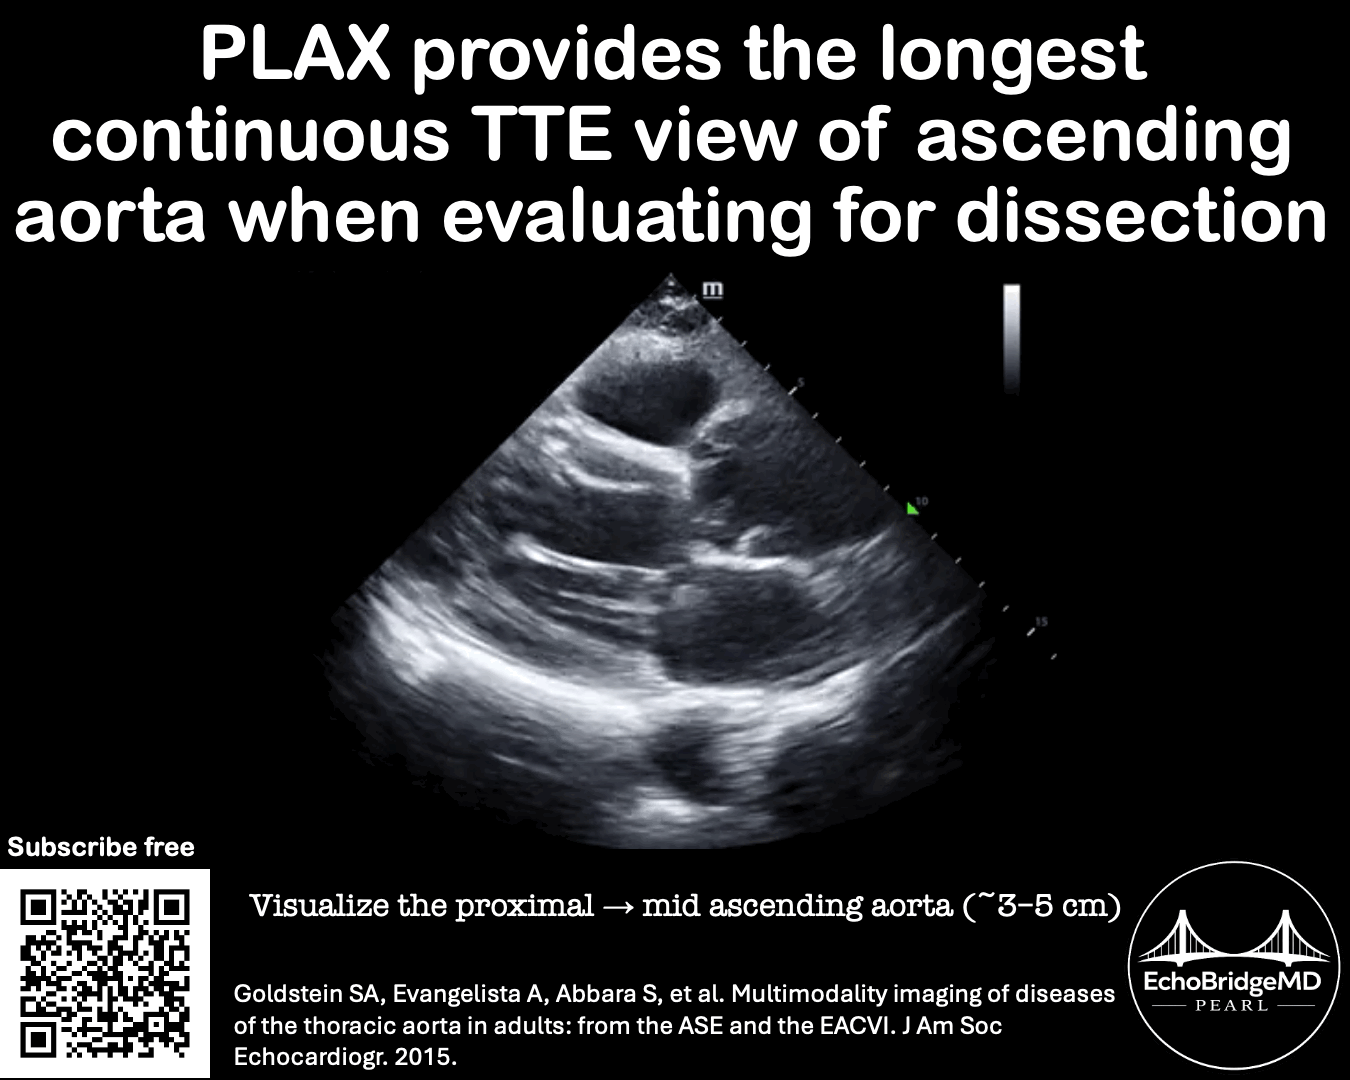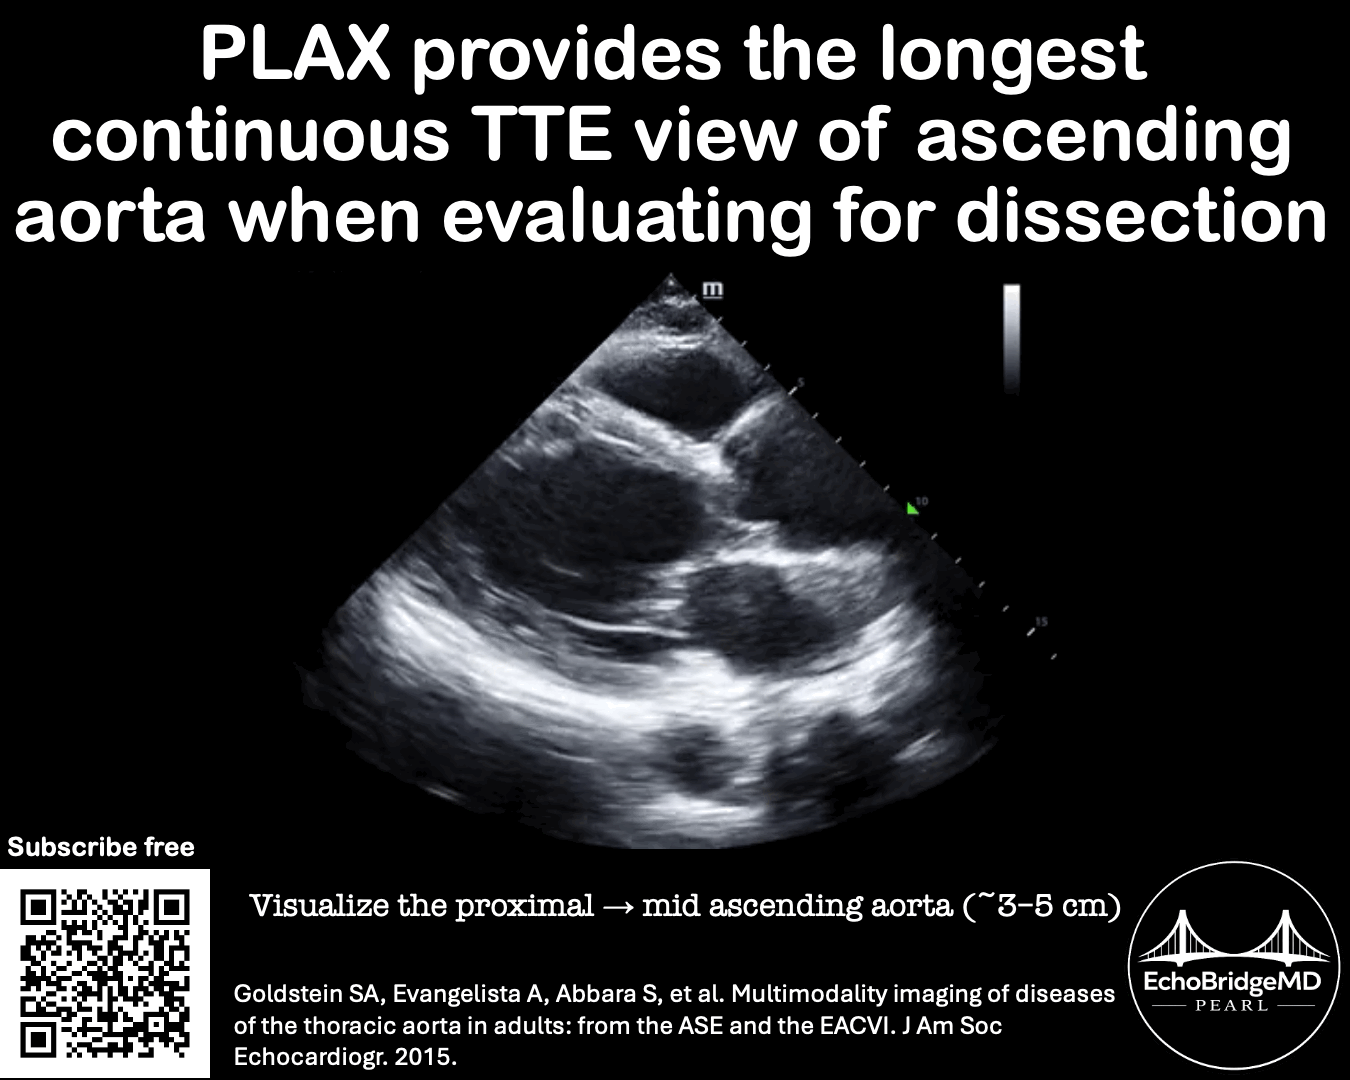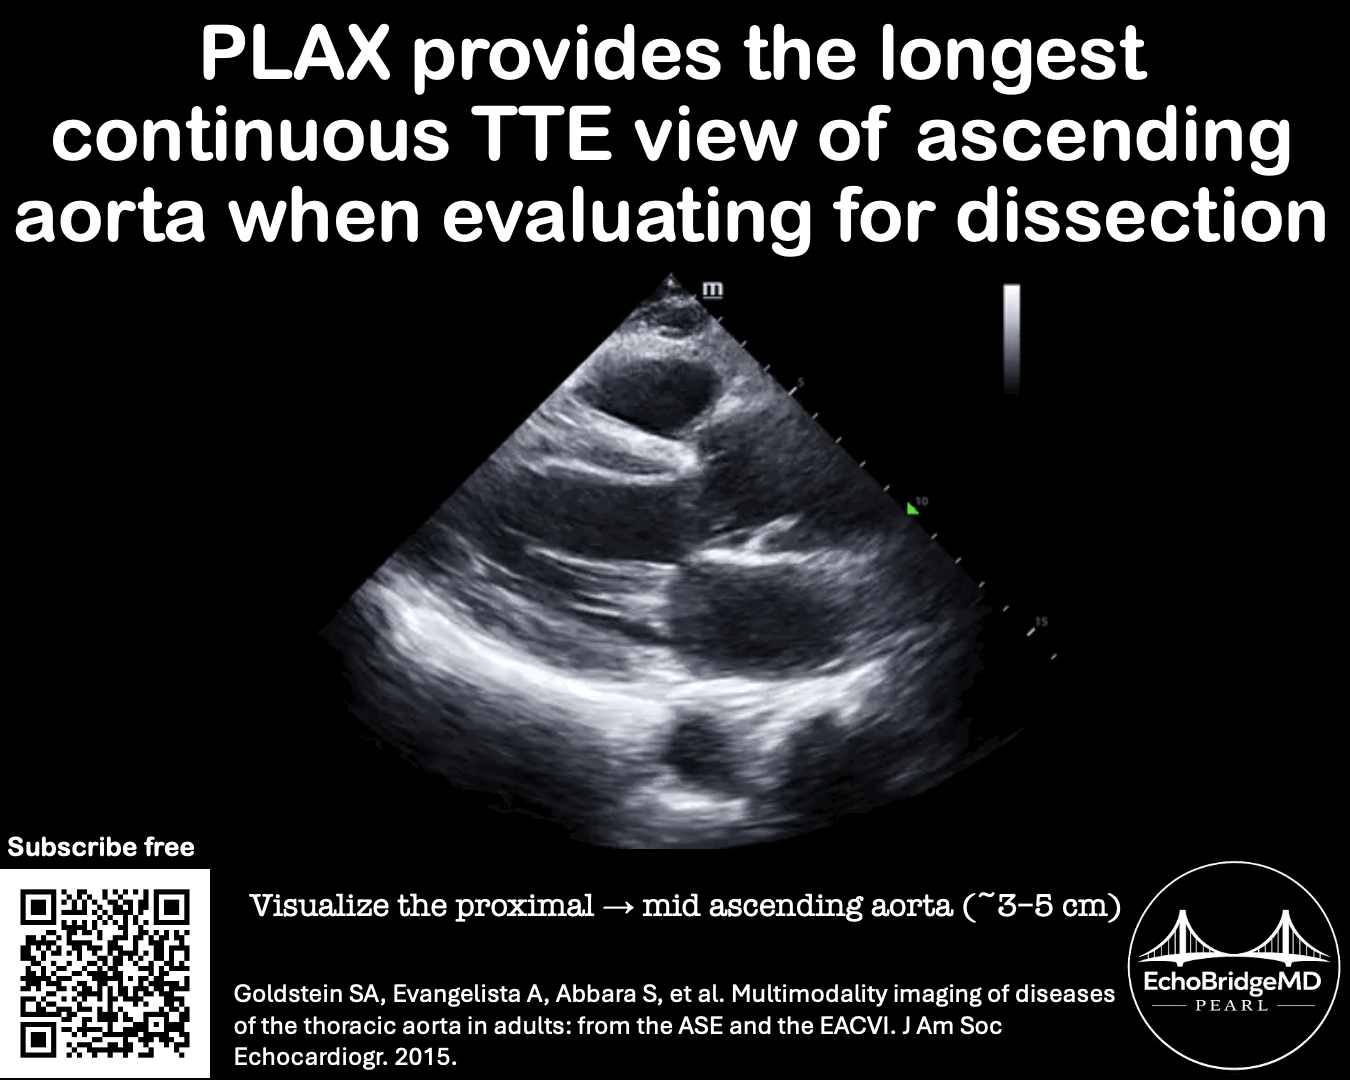
EchoBridgeMD Pearl #28: PLAX View for Type A Aortic Dissection
When evaluating for acute Type A aortic dissection with point-of-care echocardiography, the parasternal long-axis (PLAX) view provides the most extensive visualization of the ascending aorta from a single standard TTE window. The PLAX view can visualize approximately the first 3–5 cm of the ascending aorta, from its proximal to mid-portion, allowing the clinician to examine a relatively long segment for an intimal flap, aortic root or ascending aortic dilation, and other find
Stephen Alerhand
Sep 241 min read


EchoBridge Pearl #26: Left Ventricular Hypertrophy and Left Atrial Enlargement Suggest Diastolic Dysfunction
Left ventricular hypertrophy (LVH) and left atrial (LA) enlargement are important echocardiographic clues to chronic diastolic dysfunction. As the LV becomes stiffer and less compliant, LV filling pressures gradually increase, leading to chronically elevated LA pressure and progressive LA remodeling. Although neither finding is diagnostic on its own, the combination of LVH and LA enlargement should raise suspicion for heart failure with preserved ejection fraction in patients
Stephen Alerhand
Sep 171 min read


EchoBridge Pearl #25: Qualitative Assessment of Global Left Ventricular Systolic Function
Global left ventricular (LV) systolic function can be assessed accurately using a qualitative ("eyeball") approach. By integrating myocardial thickening, endocardial excursion, and overall ventricular contraction across multiple echocardiographic views, clinicians can reliably estimate global LV systolic function at the bedside. With practice, visual estimation provides rapid, clinically meaningful information that often guides immediate patient management without the need fo
Stephen Alerhand
Sep 141 min read


EchoBridge Pearl #24: Assessing Pericardial Effusions from Multiple Views
An effusion may be visible in one view but absent in another, and its apparent size can vary substantially depending on the imaging plane. Before determining the presence, size, or distribution of a pericardial effusion, systematically examine all standard cardiac windows to avoid underestimating or overestimating the effusion. In these clips, note how the pericardial effusion appears most prominent in the subxiphoid long-axis view. References: 📖 Alerhand S, Adrian RJ, Long
Stephen Alerhand
Sep 101 min read


EchoBridge Pearl #23: Right Ventricular Free Wall Thickness
The normal right ventricular (RV) free wall measures 3–5 mm thick in end-diastole (excluding trabeculations). An RV free wall thickness > 5 mm, measured from the subxiphoid or parasternal long-axis view, is consistent with RV hypertrophy. In the absence of other causes, this finding suggests chronic RV pressure overload rather than an acute process such as pulmonary embolism. Recognizing this distinction can help place RV dilation or dysfunction into the appropriate clinical
Stephen Alerhand
Sep 71 min read


EchoBridge Pearl #22: Sonographic Diagnosis of Endocarditis
On echocardiography, infective endocarditis typically appears as an echogenic mass (vegetation) attached to the valve that moves independently of the valve leaflets. Vegetations most commonly arise along the coaptation line on the lower-pressure side of the valve. After identifying a vegetation, carefully evaluate the valve for leaflet thickening, abnormal coaptation, chordal rupture, or prolapse, as these associated findings may indicate more advanced valvular destruction. ���
Stephen Alerhand
Sep 31 min read


EchoBridgeMD Evidence Update #3: TEE Reveals Where We Are Actually Compressing During CPR
Transesophageal echocardiography (TEE) may allow clinicians to assess not only cardiac activity during arrest, but also whether chest compressions are actually being delivered over the optimal cardiac location. In this prospective observational study, investigators performed point-of-care TEE immediately upon emergency department arrival in 18 patients with out-of-hospital cardiac arrest undergoing extracorporeal CPR with ongoing mechanical chest compressions. TEE successfull
Stephen Alerhand
Sep 11 min read


EchoBridge Pearl #21: Tamponade Physiology in Cardiac Arrest
In patients with spontaneous circulation, systolic right atrial and diastolic right ventricular collapse are important echocardiographic signs of cardiac tamponade. During cardiac arrest, however, the absence of normal forward flow and intracardiac pressures makes these findings much less reliable. As a result, the presence or absence of right-sided chamber collapse should not be used in isolation to determine whether a pericardial effusion is responsible for the patient's ca
Stephen Alerhand
Aug 311 min read


EchoBridge Pearl #20: B-Mode Valve Assessment
Brightness mode (B-mode) imaging is the first step in evaluating cardiac valves. A simple framework is to systematically assess three key features: 1. Excursion – How well do the valve leaflets open? 2. Coaptation – How well do the leaflets come together when closed? 3. Masses – Are vegetations, thrombi, tumors, or other abnormal structures present? Applying the same three-step approach to every valve helps ensure a complete and consistent examination. 🔗 Free subscription —
Stephen Alerhand
Aug 271 min read


EchoBridgeMD Evidence Update #2: POCUS Shows Strong Diagnostic Performance for Acute Aortic Dissection
A new systematic review and meta-analysis provides further support for incorporating POCUS into the early evaluation of patients with suspected acute aortic dissection. Across 11 included studies, bedside ultrasound demonstrated a pooled sensitivity of 86% and specificity of 84%, with diagnostic performance more favorable for Stanford Type A dissection. Visualization of an intimal flap was the most specific finding, while other echocardiographic findings can provide complemen
Stephen Alerhand
Aug 251 min read


EchoBridge Pearl #19: Differentiating True vs False Lumen in Aortic Dissection
When an intimal flap is identified, distinguishing the true lumen from the false lumen can help confirm the diagnosis and guide interpretation. The false lumen is typically larger, expands during diastole, and often demonstrates spontaneous echocardiographic contrast ("smoke") due to slower blood flow. In contrast, the true lumen is usually smaller and expands during systole as blood is ejected from the left ventricle. 📖 Goldstein SA, Evangelista A, Abbara S, et al. Multimod
Stephen Alerhand
Aug 241 min read


EchoBridgeMD Pearl #17: Pathophysiology of Diastolic Dysfunction
Normal left ventricular (LV) filling during diastole occurs when the myocardium relaxes easily and accepts blood compliantly. Early diastolic filling accounts for approximately 70–80% of LV filling, while left atrial (LA) contraction contributes the remaining 20–30%. With diastolic dysfunction, the myocardium becomes stiff and non-compliant (such as from long-standing hypertension). This leads to elevated LV filling pressures, increased LA pressure, and LA enlargement. When t
Stephen Alerhand
Aug 171 min read


EchoBridgeMD Evidence Update #1: Yet Another Study Questions the Optimal Location for Chest Compressions
Yet another study adds to growing evidence that guideline-recommended hand placement for chest compressions may not correspond to the optimal anatomic target. In this prospective ultrasound study of 152 adults, investigators used transthoracic echocardiography to identify the left ventricular outflow tract (LVOT) and the ideal area of maximal compression (iAMC), then mapped these structures onto standardized external chest-wall coordinates relative to the sternum. The LVOT wa
Stephen Alerhand
Aug 121 min read


EchoBridgeMD Pearl #15: POCUS Shortens Time to Pericardiocentesis
In patients with cardiac tamponade, earlier point-of-care ultrasound (POCUS) in the emergency department is associated with a shorter time to pericardiocentesis. Prompt bedside diagnosis can expedite definitive treatment in this life-threatening condition. References: 📖 Eke OF, et al. Timing of pericardiocentesis and clinical outcomes: Is earlier pericardiocentesis better? Am J Emerg Med. 2022. 📖 Alerhand S, Adrian RJ, Long B, Avila J. Pericardial tamponade: A comprehensive
Stephen Alerhand
Aug 101 min read
bottom of page